Choosing a hospital adjustable bed is not just a matter of adding motorized controls. The right design can support safe transfers, easier repositioning, and practical care routines. Yet hospitals serve patients with very different needs. A general medical ward, intensive care unit, and bariatric care area may require different bed features.
The American Hospital Association’s 2024 Fast Facts counted 6,120 U.S. hospitals, highlighting the scale and variety of care settings. AHRQ’s Preventing Pressure Ulcers in Hospitals toolkit reports that more than 2.5 million people develop pressure injuries each year in U.S. acute-care facilities. These figures do not prove that a particular bed prevents injury. They do show why positioning, pressure management, and staff workflow deserve careful attention.
Common options include manual, semi-electric, and fully electric beds, alongside low-height, bariatric, and intensive-care models. Each has trade-offs. Manual beds may suit basic needs, while powered models allow quicker height and position adjustments. Specialty beds can offer features such as integrated weighing or advanced rotation, but added functions need proper training and maintenance. No bed replaces attentive care. That is worth remembering.
This guide compares the top types of hospital adjustable bed by design, use case, and key features. It also considers practical details, such as rail configuration, mattress compatibility, and room space, so buyers can match equipment to patient needs rather than rely on features alone.
Manual Hospital Adjustable Beds
Manual hospital adjustable beds use a hand crank rather than an electric motor to change the bed’s position. Depending on the model, staff can raise the head section, bend the knee section, or adjust the frame height. The mechanism is straightforward. It also requires hands-on effort. For patients needing only occasional repositioning, a manual bed may be practical, especially where electrical access is limited.
AHRQ’s Preventing Falls in Hospitals toolkit estimates that 700,000 to 1 million hospitalized patients fall each year (AHRQ, 2013). This estimate does not show that one bed type prevents falls. It does highlight why transfer height, wheel locks, and clear access matter. Cranking a bed repeatedly can take time and strain caregivers, particularly during busy shifts. That trade-off is easy to underestimate. Manual beds may suit lower-acuity settings, but frequent positioning needs deserve careful review.
Tips: Before choosing a bed, test its crank with the mattress installed. Check that one caregiver can reach the required positions safely. Confirm the lowest transfer height and teach staff how to lock the wheels. A short trial with real users can reveal problems a specification sheet misses.
Semi-electric hospital adjustable beds use a motor to raise or lower the head and foot sections. A hand crank usually adjusts the bed’s overall height. This setup can offer useful positioning without powering every movement. It may suit a person who needs frequent posture changes but has less need for daily height adjustments.
Look closely at the crank location. A caregiver may need to bend beside the frame, and repeated turns can feel tiring. The electric handset should be easy to reach from the bed, with its cord kept clear of wheels and walking paths. Check the bed’s weight capacity, mattress dimensions, and compatibility with any side rails. These details vary by model.
There is a trade-off. If height needs to change often, a fully electric model may be easier to operate. During a power interruption, powered positioning may stop, so ask how that specific bed can be adjusted. Small details matter. Before choosing, discuss transfer needs and caregiver strength with a healthcare professional. A bed can look suitable in a catalog yet feel awkward in a real room. That is worth checking in person.
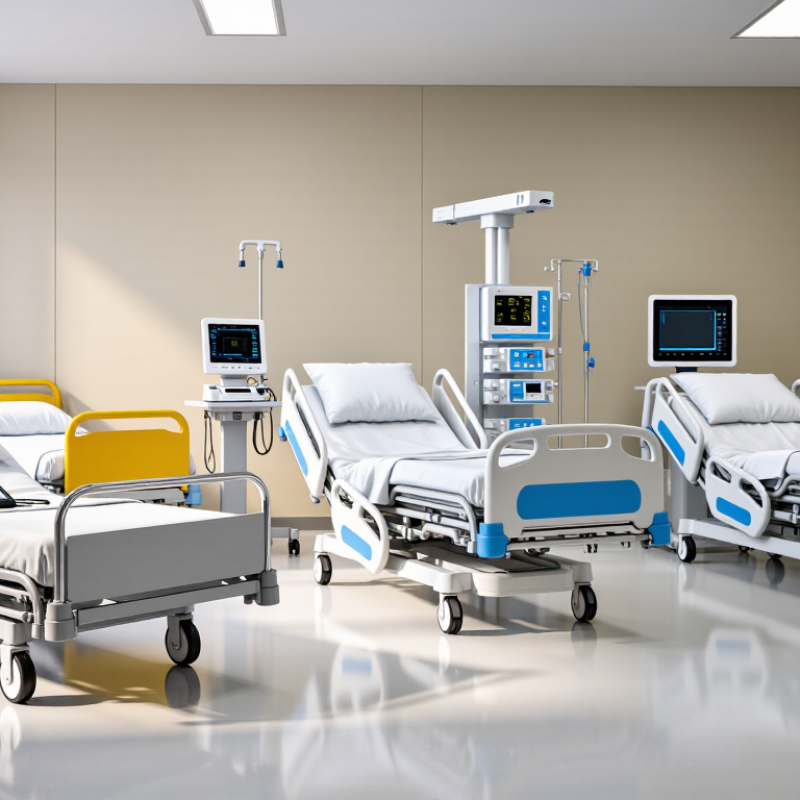
Fully electric hospital adjustable beds use motors to raise or lower the bed deck and position the back and leg sections. Staff can make these changes with a handheld pendant, rather than turning manual cranks. That matters during routine care: a nurse can bring the mattress closer to waist height for a dressing change, then lower it for a patient preparing to stand. Small detail. The height range and control layout vary, so teams should check that staff can reach the buttons and patients can use them safely.
The U.S. Bureau of Labor Statistics reported 4.5 injury and illness cases per 100 full-time-equivalent workers in healthcare and social assistance in 2022, compared with 2.7 across private industry. These sector-wide figures do not prove that powered beds prevent injuries. They do show why reducing awkward bedside work deserves attention. Powered height adjustment may help staff avoid repeated bending, but it cannot replace safe transfer techniques or hands-on assistance. A low position can also make standing harder for some patients. Fit the bed to the person, not just the room. The BLS report is Employer-Reported Workplace Injuries and Illnesses, 2022.
Bariatric Hospital Adjustable Beds
Bariatric hospital adjustable beds are designed for patients who need a wider sleep surface, greater weight capacity, or more room for transfers. They may include reinforced frames, expanded decks, and controls that raise the head and knees. Capacity varies by model, so staff should check the rated safe working load rather than rely on the word “bariatric.” Fit matters. A wide bed that is difficult to maneuver can complicate care and room access.
The CDC’s National Center for Health Statistics reported that 40.3% of U.S. adults had obesity and 9.4% had severe obesity between August 2021 and August 2023 (Data Brief No. 508, 2024). These population figures do not determine an individual patient’s bed needs. They do underline the value of having suitable equipment available. Check weight ratings, mattress dimensions, rail compatibility, and clearance for patient lifts. OSHA guidance also supports using mechanical lifting equipment when appropriate.
Bed selection should account for mobility, skin risk, patient preference, and transfer needs—not weight alone. Assess bed height, controls, and side rails for the specific patient. Confirm that the mattress suits both the frame and the care plan. Easy to miss. Measure doorways and turning space before delivery, and check access for emergency equipment. Specifications can look reassuring on paper; actual room setup may tell a different story.
Bariatric adjustable beds are available in a range of weight-capacity ratings. The chart shows example capacity tiers, not standardized bed types or a guarantee for any specific model.
Choose a bed based on its manufacturer-listed safe working load, which includes the patient and any supported equipment. Capacity, frame width, and adjustment features vary by model.
Pediatric hospital adjustable beds are sized and configured for a child’s body, mobility, and stage of development. A lower minimum height can make transfers easier for caregivers and reduce the distance to the floor. Carefully designed side rails help limit gaps where a child could become trapped. The right setup depends on the child’s size and care plan, not simply age.
Small details matter. Check that the mattress fits the frame without open spaces, and that controls are reachable only by the intended user. Children with limited mobility may need supportive positioning, while some beds offer built-in weighing functions or surfaces that redistribute pressure. These features can support care, but they do not replace assessment and guidance from the clinical team.
Specialty beds may also serve patients with complex movement or positioning needs. A low-height frame, adjustable sections, or a compatible pressure-redistribution mattress can make daily care more manageable. Staff should confirm that accessories work with the bed and do not interfere with rails or controls. A feature list can look reassuring, yet the room layout and caregiver workflow sometimes get overlooked. Test those practical details before choosing a configuration.
| Bed Type | Typical Patient or Setting | Common Adjustable Features | Key Safety or Care Considerations |
|---|---|---|---|
| Pediatric hospital bed | Children who need inpatient care, monitoring, or assistance with positioning. | Depending on the model, may offer powered height and deck adjustment, adjustable head and knee sections, and enclosed or height-adjustable side rails. | Rails and gaps should be appropriate for the child’s size and developmental stage. Care teams should assess entrapment and climbing risks. |
| Pediatric crib or enclosed pediatric bed | Infants and young children who need a secure hospital sleep space. | Some models have adjustable mattress platforms or height settings; access panels or sides may open for caregiver access. | Use an age- and size-appropriate sleep surface and follow the facility’s guidance for positioning, restraints, and monitoring. |
| Adolescent bed | Older children and teenagers who may need a larger sleeping surface than a pediatric crib provides. | May include adult-style electric positioning and height adjustment, with dimensions and rail configuration selected for the patient. | Choose the bed and accessories based on the patient’s height, weight, mobility, and ability to use controls safely. |
| Low hospital bed | Patients at increased risk of injury from falling out of bed, when a low bed is part of the care plan. | Designed to lower the sleeping surface closer to the floor; many models also adjust the head, knee, or overall bed height. | A low bed does not prevent falls. Consider the patient’s transfer needs, floor-level hazards, and other individualized fall-prevention measures. |
| Bariatric hospital bed | Patients whose weight or body dimensions require a wider, higher-capacity bed. | Often features a wider frame, reinforced construction, and powered adjustments. Weight capacity and usable width vary by model. | Confirm the bed’s stated safe working load and width, including the capacity of the mattress and accessories. Plan for suitable transfer equipment. |
| Critical-care or ICU bed | Patients in intensive care who require frequent repositioning, close observation, or support for clinical procedures. | May provide powered positioning, height adjustment, and, on selected models, Trendelenburg or reverse Trendelenburg positioning. | Features vary. Positioning should be directed by trained clinical staff and coordinated with monitoring equipment, tubing, and patient condition. |
| Specialty positioning bed | Patients who need particular positioning support for treatment, mobility limitations, or pressure-injury prevention plans. | May include programmable positions, articulated sections, or compatibility with specialized support surfaces. | A bed alone does not prevent or treat pressure injuries. Select the surface and repositioning approach with the clinical team. |
Note: Available functions, dimensions, and weight limits differ by model. Bed selection should be based on the patient’s needs, the intended care setting, and the manufacturer’s specifications.